Friday, September 25, 2026

Premature Death and Dying Too Young by Keith Torkelson MS, BS


Contents


Requirements
Results up Front - Count Summary
Define Dying Too Young
Statistically Normal Life
Statistical Cure for Mental Illness
Resolving Mental Illness by doing Normal Things
Features of Dying Too Young
What age is premature Death?
Dying Too Young in a War
Total Number of People that died in war?
Assignments for a Thanotologist
Tangent - Define Dying Old Men (DOMs)
Nature DBO = Death by Other - Impact
AD = Accidental Death
DBEN = Death by Exhaustion and/or Neglect
DEATH by Exhaustion and/or Neglect
Inappropriate Service
What does it mean to be inappropriately served?
Table – Those Who: Died Too Young (DTY) – KIA
Self-inflicted Death
Principles of Suicide prevention
Define Overtly Dead
Is Death a Power Greater Than Us?
MIA List
Images @ the End – Cemetery and MIA


Define Dying Too Young

Dying too young means losing a life prematurely, before reaching middle or old age, or before experiencing a statistically normal lifespan.

Key Aspects of the Concept

Untimely End:

It refers to passing away well before expected life milestones are met.

Unfulfilled Potential:

The phrase emphasizes the loss of future experiences, career goals, or family milestones.

Emotional Impact:

Such deaths often evoke a deep sense of tragedy, shock, and sorrow among family members and society.

Common Causes:

These premature losses frequently result from sudden accidents, severe illnesses, or unexpected violence rather than natural old age.


FYI – AI - If you'd like, I can provide: Statistics on average life expectancy. Information on how societies process untimely grief


Statistically Normal Life

A statistically normal life expectancy in the United States is 79.0 years overall, with 81.4 years for females and 76.5 years for males.

Key Statistical Life Metrics

Global Context:

Worldwide life expectancy at birth averages around 72 to 73 years, a major increase from about 31 years in 1900 due to better medicine and public health.

Maximum Lifespan:

While average life expectancy measures the mean age of survival, the maximum recorded human lifespan reaches up to 122 years.

Variability:

Geography, income, and education shift these numbers significantly; for instance, state averages in the U.S. can vary by nearly a decade depending on location.

Social Norms:

Beyond biology, statistical "normality" in human behavior and lifestyle shifts across generations as cultural and societal trends evolve.


Statistical Cure for Mental Illness

In medicine, mental illnesses are managed rather than statistically "cured," as most chronic psychiatric conditions focus on achieving remission rather than a permanent, zero-recurrence reversal.

Treatment and Remission Statistics

Adult Treatment Rates:

Approximately 52.1% of U.S. adults with any mental illness and 70.8% with a serious mental illness receive treatment annually, according to data from National Alliance on Mental Illness (NAMI).

Global Effective Treatment Gap:

Worldwide, an estimated 6.9% of people with mental health or substance-use disorders receive effective treatment, with a major barrier being lack of recognition that care is needed.

Remission vs. Cure:

Clinical definitions separate symptom remission (symptoms resolving temporarily or long-term) from a medical cure, because conditions like major depression, bipolar disorder, and schizophrenia carry a baseline risk of recurrence or relapse.

Annual Interventions:

Recent Centers for Disease Control and Prevention (CDC) Data Briefs show that roughly 19.3% of U.S. adults use prescription medication and 14.0% utilize counseling or therapy in any given 12-month period.


Resolving Mental Illness by doing Normal Things

Yes, engaging in standard, daily "normal things"—often referred to in medicine as lifestyle medicine or behavioral activation—is a powerful, scientifically proven way to manage and reduce symptoms of mental illness. While severe clinical conditions frequently require professional treatments like therapy or medication, everyday habits act as the foundation for chemical stability and neurological health in the brain.

Here is how routine, "normal" activities directly combat mental illness:

1. Physical Movement

The "Normal" Action:

Taking a daily 30-minute walk, cleaning the house, or taking the stairs.

The Biological Impact:

Exercise regulates neurotransmitters like serotonin and dopamine, which dictate mood and motivation. According to research shared by the American Psychiatric Association, routine movement is an effective primary or supporting treatment for depression, anxiety, and PTSD.

2. Social Connection

The "Normal" Action:

Having coffee with a friend, calling a family member, or volunteering.

The Biological Impact:

Human brains are wired for connection. Isolation tricks the brain into a state of chronic physiological stress. Interacting with others signals "safety" to the nervous system, lowering cortisol (stress hormone) levels and triggering the release of oxytocin.

3. Sleep Architecture

The "Normal" Action:

Going to bed and waking up at the exact same time every day.

The Biological Impact:

Sleep directly manages emotional resilience. Chronic sleep disruption impairs the prefrontal cortex, which handles emotional regulation. Sticking to a strict sleep schedule helps the brain process emotional trauma and daily anxiety effectively.

4. Behavioral Activation (Doing it anyway)

The "Normal" Action:

Getting out of bed, showering, making a meal, or participating in a hobby even when you don't feel like it.

The Biological Impact:

Mental illnesses like depression trick the brain into a cycle: Feel bad → isolate/stay in bed → feel worse. Doing normal tasks breaks this loop by forcing "opposite-to-emotion" behavior, proving to your brain that you can experience competence and control.

5. Nature and Environmental Shifts

The "Normal" Action:

Sitting under a tree, stepping into the sunlight first thing in the morning, or working out of a coffee shop.

The Biological Impact:

Sunlight regulates your circadian rhythm, which governs mood-lifting hormones. According to mental health insights from the NHS, environments with natural elements rapidly decrease blood pressure and nervous system hyper-arousal.


Features of Dying Too Young

Dying at a young age often involves a longer, more physically resistant dying process and complex emotional challenges compared to passing away at an advanced age.

Physical Features and the Dying Process

Stronger bodily reserves:

Younger individuals typically possess stronger hearts, lungs, and physical reserves, which can cause the body to sustain vital functions longer even during advanced organ failure.

Prolonged decline:

Because otherwise healthy organs resist shutting down, the active dying process can involve a more extended period of physical strain and symptoms.

Universal end-stage signs:

In the final stages, younger individuals experience similar physical signs of active dying as older adults, such as irregular breathing patterns (like Cheyne-Stokes respiration), cooling extremities, increased drowsiness, and difficulty swallowing.

Emotional and Psychological Features

Perception of injustice:

The death of a young person is widely viewed as tragic and untimely, which can lead to intense emotional resistance and grief from both the individual and their family.

Extended suffering:

The emotional toll often includes profound frustration and a prolonged sense of unfairness regarding unfulfilled life milestones.

Support focus:

Care for younger individuals nearing the end of life centers heavily on respecting personal autonomy, managing complex symptoms, and addressing heavy psychological distress.


FYI – AI - If you are looking for information on a specific condition, age group, or palliative care strategy, let me know so I can provide more tailored details.


What age is premature Death?

Premature death is generally defined as a death that occurs before the age of 75, though some health groups use age 65.

Age Standards

Age 75:

The Centers for Disease Control and Prevention (CDC) and America's Health Rankings use age 75 as the standard cutoff. This matches the average life expectancy in the United States.

Age 65:

Some researchers use age 65 to measure early or untimely deaths.

Life Expectancy:

Other studies compare the exact age of death to the expected life span of a specific group.

Common Causes

According to the National Cancer Institute, many early deaths come from preventable or treatable health issues:

  • Unintentional injuries (accidents)
  • Cancer
  • Heart disease
  • Suicide
  • Stroke


Note – For the purposes of this study we set the age of premature death at 70 years old or less.


Dying Too Young in a War

Older political leaders declare wars, but young soldiers bear the physical and emotional cost of fighting and dying on the battlefield.

Historical Sentiments and Quotes

Herbert Hoover:

Stated in a 1944 speech that "Older men declare war. But it is youth that must fight and die".

Popular Culture:

The 2004 film Troy popularized the line "War is old men talking and young men dying".

Rudyard Kipling:

Wrote in 1918, “If any question why we died, tell them, because our fathers lied”.

Why Young People Fight

Physical Fitness:

Military organizations generally recruit younger individuals because of their strength, quick reflexes, and endurance.

Generational Disconnect:

Decision-makers in government are typically older and remain safe from direct combat.


Total Number of People that died in war?

It is impossible to calculate a definitive total number of people who have died in all human wars throughout history due to missing ancient records, poor data collection, and unrecorded smaller conflicts.

However, broad historical estimates and data trackers provide a sense of the scale:

Historical Estimates

Recent Centuries:

According to Our World in Data, more than 37 million people have died fighting in wars since 1800. This number excludes many civilian casualties and war-related famines.

All-Time Estimates:

Some wide-ranging historical estimates suggest that anywhere from 35 million (for focused modern periods like 1816–2007) up to 1.5 billion to 2 billion people have died across all of human history when including indirect war-related famines, diseases, and ancient conflicts.

Deadliest Conflicts in History

World War II (1939–1945):

The deadliest military conflict in human history, resulting in an estimated 70 to 85 million total deaths (including 50–55 million civilians and 21–25 million military personnel from all causes, such as combat, disease, and famine).

World War I (1914–1918):

Resulted in an estimated 15 to 20 million deaths, split roughly evenly between military personnel and civilians, plus millions more missing or dead from disease.

Other Major Tolls:

Historical catastrophes like the List of wars by death toll estimate hundreds of thousands to millions of deaths in regional conflicts like the Taiping Rebellion, Mongol conquests, or the Second Sino-Japanese War.


FYI – AI - If you'd like, I can break down the numbers further for: A specific century or era

Specific major wars (like the American Civil War or WWI). Military vs. civilian casualty ratios.


Assignments for a Thanotologist

Thanatologists—professionals who study the psychological, social, and physical aspects of death, dying, and bereavement—take on dynamic assignments depending on their specific subspecialty. Their work spans clinical practice, academic research, community advocacy, and funeral operations.

Clinical & Bedside Care Assignments

Anticipatory Grief Counseling:

Working with patients who have received terminal diagnoses and their families to navigate emotional transitions before death occurs.

End-of-Life Legacy Planning:

Helping individuals author ethical wills, record oral histories, or curate memory books for their loved ones.

Vigil Accompaniment:

Providing a calm, non-medical presence at the bedside of actively dying patients—a common assignment for death doulas and hospice team members.

Symptom Comfort through Art:

Developing customized sensory interventions, such as utilizing bedside live music therapy, to reduce anxiety during the transition.

Grief Support & After-Loss Administration

Complicated Grief Therapy:

Facilitating therapeutic interventions for individuals experiencing traumatic, unexpected, or prolonged bereavement.

Support Group Facilitation:

Organizing and leading specialized community healing cohorts, such as groups tailored for grieving parents, veterans, or children.

Bereavement Care Assessment:

Evaluating surviving family members to identify individuals at high risk for clinical depression or physical health decline following a loss.

Post-Death Benefits Guidance:

Assisting families with immediate administrative tasks, including processing legal documents, navigating death benefits, and filing claims.

Funeral and Deathcare Operations

Custom Ceremony Curation:

Interviewing the bereaved to construct highly customized and culturally respectful funeral ceremonies and obituaries.

Restorative Arts & Preservation:

For thanatologists dual-certified as embalmers or thanatopractors, analyzing chemical and biological data to preserve and dress the deceased for open-casket viewings.

Academic, Research & Community Advocacy

Death Literacy Education:

Preparing and delivering community educational workshops, university curriculum, or open forums like "Death Cafés" to destigmatize mortality.

Sociological and Historical Research:

Conducting empirical field studies on how evolving social landscapes, virtual mourning trends, and diverse cultures shape modern perceptions of loss.

Medical Ethics Consulting:

Serving on hospital or corporate panels to advise on systemic protocols regarding euthanasia, physician-assisted care, or institutional living wills.


Tangent - Define Dying Old Men (DOMs)

For this study Dying Too Young (DTY) is dying before the age of 70.  A dying old man is not defined by age rather by functionality, Quality of Life (QOL) and Life’s Satisfaction.  We use various assessments to characterize DOMs.  DOMs usually score lower than 70% or so with their Activities of Daily Living Basic 10 Item Screener.  They have few Extended Activities of Daily Living such as literacy or working with computers.  A common feature of DOMs is when they lose the ability to walk by themselves.  If Buster can’t walk anymore he very likely will desire to be put-to-sleep (See POLST).  Many DOMs tend to be angry and have few plans.  An example of a dying old man was Al. 


Table – Those Who: Died Too Young (DTY)
Nature DBO = Death by Other - Impact
PII = Personally Identifying Information


Last Reviewed: 20260924-TH:


Table – Those Who: Died Too Young (DTY)
AD = Accidental Death
PII = Personally Identifying Information


Table – Those Who: Died Too Young (DTY) - Sample
DBEN = Death by Exhaustion and/or Neglect


DEATH by Exhaustion and/or Neglect

Exploring an intense and heavy concept, whether for a creative writing project, a character backstory, or an educational research topic. Here is a breakdown of how exhaustion and neglect function as causes of death, focusing on the biological and physiological realities.

Death by Exhaustion (Inanition / Physical Collapse)

In medical and forensic terms, pure exhaustion rarely kills on its own; instead, it triggers a systemic failure of the body's vital organs.

Cardiac Arrest:

Extreme physical overexertion without rest places immense stress on the heart. The cardiovascular system eventually collapses, leading to fatal arrhythmias.

Organ Failure:

Prolonged lack of sleep or continuous physical labor prevents the body from repairing tissue. This causes a buildup of toxins, eventually leading to kidney or liver failure.

Immune Collapse:

Severe exhaustion completely decimates the immune system, making the body vulnerable to minor infections that quickly turn fatal (like sepsis).

Death by Neglect (Deprivation / Failure to Thrive)

Death by neglect is categorized by the withholding of basic human needs over a prolonged period.

Dehydration:

The fastest fatal element of neglect. Without water, the kidneys fail, blood volume drops, and hypovolemic shock or cardiac arrest occurs within days.

Malnutrition / Starvation:

The body begins consuming its own fat, then muscle tissue, and eventually its own organs to survive. Death usually occurs from heart failure when the heart muscle becomes too weak to pump blood.

Exposure:

Left in unsafe environments, the body succumbs to hypothermia (extreme cold) or hyperthermia (extreme heat), which rapidly shuts down the central nervous system.

The Combination:

The Feedback Loop

When exhaustion and neglect occur together, they accelerate one another. A neglected body lacks the calories and hydration needed to recover from physical exertion. Conversely, an exhausted body cannot seek out the resources it needs to survive, leading to a rapid downward spiral.

 
Inappropriate Service

The Wasteful and Inappropriate Service Reduction (WISeR) Model is a federal pilot program by the Centers for Medicare & Medicaid Services (CMS) designed to target low-value, costly medical services vulnerable to overuse, waste, fraud, and abuse.

How WISeR Works

Prior Authorization:

Healthcare providers must request prior approval from Medicare before giving patients certain targeted services.

Technology Use:

The program uses Artificial Intelligence (AI) and human clinical reviews to speed up and manage prior authorization decisions.

Timeline:

The pilot program launched on January 15, 2026, and is scheduled to run through December 31, 2031.

Locations:

It is mandatory only for Original Medicare beneficiaries in six states: New Jersey, Ohio, Oklahoma, Texas, Arizona, and Washington. Medicare Advantage plans are not included.

Targeted Services

  • The model requires prior authorization for about 17 specific low-value or frequently overused services, including:
  • Skin and tissue substitutes
  • Electrical nerve stimulators
  • Knee arthroscopy for knee osteoarthritis
  • Certain spine decompression and orthopedic pain management procedures, such as cervical fusion and steroid injections


What does it mean to be inappropriately served?

Being inappropriately served medically means receiving healthcare that is harmful, unethical, clinically unnecessary, or below professional standards. This concept usually falls into one of three major categories depending on the nature of the care:

1. Medically Unnecessary Care (Overtreatment)

This happens when a patient receives treatments, tests, or procedures that offer no reasonable benefit or where the risks outweigh the rewards.

Unwarranted Procedures:

Performing surgeries or diagnostic tests that have no clinical indication.

Overprescribing:

Providing medications, like unnecessary antibiotics for a viral infection, that can cause side effects without treating the cause.

Financial Drivers:

Administering services primarily to boost provider revenue or insurance billing rather than to help the patient.

2. Substandard Care (Improper Treatment or Omission)

This occurs when the care provided fails to meet accepted medical guidelines, commonly referred to as the standard of care.

Misdiagnosis:

Failing to correctly identify a condition, which delays appropriate therapy and allows an illness to worsen.

Medication Errors:

Administering the incorrect dosage or a drug that interacts dangerously with a patient's medical history.

Inadequate Monitoring:

Failing to watch a patient closely after a major procedure or surgery.

3. Unprofessional or Unethical Conduct

This involves a breach of the trust, boundaries, or dignity required in a patient-provider relationship.

Lack of Informed Consent:

Performing medical actions without fully explaining the risks, benefits, and alternatives to the patient.

Discrimination:

Providing unequal or biased care based on a patient's race, gender, age, or background.

Boundary Violations:

Behaving in a demeaning, offensive, or abusive manner during examinations.


Table – Those Who: Died Too Young (DTY) - KIA

SID = Self-Inflicted Death - Ledger


Self-inflicted Death

Self-inflicted death, or suicide, is defined as death caused by injuring oneself with the explicit intent to die.

Core Nature and Characteristics

Intent and Awareness:

Clinically and legally, suicide requires conscious or semi-conscious self-directed action coupled with an intention to end one's life. This distinguishes it from accidental injury or non-suicidal self-injury, where an individual may harm themselves without an underlying wish to die.

Psychological Pain:

Experts conceptualize the act not as a physical failure of the body, but as an overwhelming response to severe psychological distress, hopelessness, or a breakdown in coping mechanisms during a crisis.

Multifactorial Risk:

Roughly 90% of individuals who die by suicide experience an underlying mental health condition, such as major depression or substance use disorder, frequently compounded by acute environmental triggers like financial loss or relational distress.

Global Impact and Prevention

Statistics:

Over 720,000 people die by suicide globally each year, making it a leading cause of mortality across various age groups, particularly young adults.

Support and Intervention:

Suicidal behaviors are preventable through timely, evidence-based public health interventions, limiting access to lethal means, and providing mental health support.


If you or someone you know is struggling or in crisis, help is available. You can call or text 988 or chat at 988lifeline.org in the United States and Canada to reach the Suicide & Crisis Lifeline.


Principles of Suicide prevention

Suicide prevention relies on a public health approach that builds safe environments, teaches coping skills, restricts access to lethal means, and connects people in crisis to immediate help like calling or texting the 988 Suicide & Crisis Lifeline. If you or someone you know is struggling or in crisis, help is available. You can call or text 988 (available 24/7, free, and confidential in the United States and Canada).

Key Principles of Suicide Prevention

1. Create Safe and Healthy Environments

Build stable communities:

Promote strong social connections, stable housing, and financial security to reduce daily stress and isolation.

Foster supportive spaces:

Help schools, workplaces, and families create open, kind cultures where people feel safe talking about mental health.

2. Teach Coping and Problem-Solving Skills

Build resilience:

Teach children and adults how to handle strong emotions, solve conflicts, and manage life challenges.

Encourage help-seeking:

Teach people to recognize when they feel overwhelmed and make it easy to ask for help without shame.

3. Identify and Support People at Risk

Recognize warning signs:

Watch for signs of distress, such as talking about feeling hopeless, talking about wanting to die, withdrawing from friends, or giving away personal items.

Train gatekeepers:

Teach community members, teachers, and managers how to spot people at risk and safely connect them with professional care.

4. Reduce Access to Lethal Means

Secure dangerous items:

Put physical space between a person in crisis and things they could use to harm themselves.

Lock up dangerous objects:

Safely store firearms in gun safes with locks, and keep prescription medications locked away to prevent impulsive attempts.

5. Provide Effective Care and Treatment

Offer targeted treatments:

Use evidence-based therapies (such as specialized counseling that focuses directly on lowering suicide risk).

Follow up after a crisis:

Provide regular check-ins and medical support after a person goes through a mental health emergency or makes an attempt.

6. Support Survivors of Suicide Loss (Postvention)

Help families heal:

Offer bereavement counseling, support groups, and debriefing sessions for people who have lost a loved one to suicide.

Reduce future risk:

Providing support to survivors helps lower the higher risk of suicide that can happen after losing someone close to you.


Define Overtly Dead

"Overtly dead" describes a state of death that is completely obvious, unmistakable, and open for everyone to see, leaving no doubt that life has ended.

Meaning and Breakdown

Overtly:

Done or shown in an open, clear, and obvious way without any attempt to hide it.

Dead:

No longer alive; lifeless.

Combined:

It refers to a situation where signs of death (such as decapitation, rigor mortis, or decomposition) are immediately and unmistakably apparent. In medical or emergency contexts, it means a patient is visibly deceased without needing complex tests to confirm.


Is Death a Power Greater Than Us?

Death is a physical power that can end human life, but it is not greater than the enduring power of love, faith, or spiritual resurrection.

The Physical Power of Death

Ends the body:

Death has the absolute biological power to stop a physical life.

Universal reality:

Every living person faces the certainty of physical death.

Inescapable limit:

No human can permanently stop or reverse physical aging and dying on their own.

What Death Cannot Control

Cannot kill love:

Death takes a physical body, but it cannot erase the love or bonds built during life.

Relationship continues:

Memories, lessons, and emotional connections stay alive in the people left behind.

Not the final word:

Many belief systems teach that human existence does not vanish completely into nothingness.

The Spiritual and Religious View

Conquered by faith:

Many major religions, especially Christianity, teach that God holds a power far greater than death.

Victory over the grave:

Believers hold that Jesus Christ defeated death through his resurrection, removing its permanent grip.

A passage, not an end:

For those with faith, death is viewed as a temporary transition or a doorway into eternal life rather than an unbeatable master.


KIA = Killed in Action is another way of saying suicide or self-inflicted harm.

MIA = Missing in Action is another way of saying we lost track of someone.


Situation 

  • Know in person
  • Not known in person yet had impact


MIA List


Sam I Am!
Mark Allen
Dave Dart
Devon V.
Greg Morgan
Rodney Spink
Robert Knutesen (Knuteson or Knutsen)
Deron Kemp


Images @ the End – Cemetery and MIA


Friday, September 18, 2026

Competency Study for End-of-life Decisions VTorkel


Outline


  • Requirements
  • Assessment Summary – Results up Front
  • Assessment Register - Origins
  • Legal MAiD Competency
  • Rational Decision Making
  • Competence & Mental Status
  • Scoring - Binary Plus Scoring Key and Scales
  • MAiD Competence Evaluation 17 Items
  • Competence of Helpers
  • Oswaldo Escalante
  • External Quality Review
  • The Clinic – Central City Community Health Center – Garden Grove
  • Martha Gil
  • Bios and Profile – Keith Torkelson, MS, BS
  • Progressive Competency 16 Items
  • Progressive Competency 15 Items
  • Progressive Competency Performance 18 Items
  • Progressive Stages 6 Items
  • Progressive Competency Gaps 27 Items
  • Partnership RDA Version Summary of 16 Items
  • FYI - Mental Health Assessment (2012 - 208 Pages)
  • The Meaning of Redacted
  • Informed Consent – Competence
  • LPS Conservatorship
  • Competency Content
  • Why are skilled nursing facilities locked facilities?
  • Mental Health Assessment
  • Mini Mental State Examination
  • Appendix – BHSA Vision Mission Values
  • Appendix – Acronyms


P&D = Progressive and Dynamic
 
Associated with > In House > Metadata >
Assess_Partnership_RDA_16070202_Gibbs V2019
MHSA_INN_HAB_18121302_VMV 2025


Feature Assessment

HHS-P-VMV  HHS-P-Value – Mission - Vision       OCHCA-MHSA


Legal - MAiD Competency

Medical Assistance in Dying (MAiD) competency requires the patient to have the decision-making capacity to understand their medical condition, the nature of MAiD, its irreversibility, and alternatives. Assessors (physicians/nurse practitioners) must confirm voluntary, informed consent without coercion, assessing for cognitive impairments that may affect judgment.


Key Aspects of MAiD Competency Assessment

Capacity Definition:

Patients must demonstrate the ability to understand information relevant to their medical condition, potential treatments, and the consequences of choosing MAiD.

Contextual Evaluation:

Capacity is decision-specific, not global. It focuses on whether the person understands what MAiD is and what their request means.

Assessing Capacity:

If capacity is questionable, a specialized assessment (e.g., psychiatrist, psychologist) may be required.

Timing:

The patient must possess the capacity to make the request, but legal standards for capacity at the very moment of the procedure (final consent) can vary based on legislation.

Clinical Competencies for MAiD Providers:

Knowledge of Regulations:

Thorough knowledge of current MAiD legislation, professional obligations, confidentiality, and informed consent is essential.

Interpersonal Skills:

MCCs (MAiD Care Coordinators) must effectively communicate and handle the emotional, ethical, and cultural complexities of the process.

Documentation:

Accurate, detailed documentation of the request, assessment, and consent is mandatory.


Note:

In Canada, if the only medical condition is a mental illness, eligibility for MAiD is not available until March 17, 2027.


MAiD Medication

Medical Assistance in Dying (MAID) utilizes specialized, high-dose medication protocols to cause peaceful, rapid death, typically within 1–2 hours. Common protocols involve a combination of drugs—often Midazolam (sedation), Propofol (coma), and Rocuronium (muscle paralysis)—or mixtures containing digoxin, diazepam, morphine, and amitriptyline.


Communication of choice

"Communication of choice" refers to selecting the most effective method, channel, or style—such as verbal, non-verbal, visual, or written—to convey messages, build relationships, and ensure clarity, particularly within organizational leadership, personal, or AAC (Augmentative and Alternative Communication) contexts. It is a strategic, often conscious decision used to minimize misunderstandings and maximize impact.


Understanding of information - Data, Information, Knowledge and Wisdom

Understanding information involves Information Literacy—the skills to find, evaluate, and use information ethically—and Cognitive Processing—how we connect new data to existing knowledge to form understanding. It requires recognizing information's context, creation, and purpose (like in the Information Cycle), understanding different types (fact vs. opinion, popular vs. scholarly), and developing habits like persistence to navigate the vast digital landscape effectively.


Appreciation of One’s Situation & Risks/Benefits of Choices Made

Appreciation of one’s situation, a key component of decision-making capacity, involves understanding the personal significance, risks, and consequences of choices. It requires evaluating options against one's own values and context, moving beyond mere understanding to grasp how a decision affects one's future. This skill is crucial for informed consent and navigating complex high-stakes decisions.


Rational decision-making

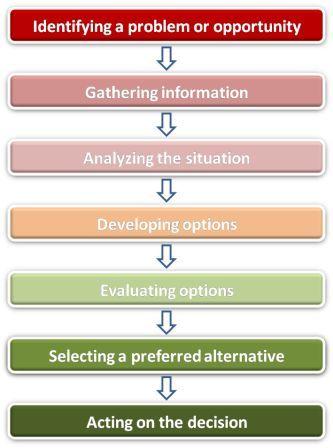
Rational decision-making is a structured, step-by-step process for making logical, data-driven choices that maximize positive outcomes and minimize risk. It involves defining the problem, identifying criteria, weighing alternatives, and selecting the best option based on facts rather than emotions. This model is ideal for high-stakes, complex decisions.


Rational Decision Making Model

Online > Metadata

https://the-happy-manager.com/article/rational-decision-making-model/

https://the-happy-manager.com/wp-content/uploads/rational-decision-making-model1.jpeg


1: Identifying a problem or opportunity

The first step is to recognize a problem or to see opportunities that may be worthwhile. A rational decision making model is best employed where relatively complex decisions have to be made.

(So the first decision making lesson should be to ask yourself if you really have a problem to solve or a decision to make. Then read this article for more specific advice: Problem Solving Skill: Finding the Right Problem to Solve).

2: Gathering information

What is relevant and what is not relevant to the decision? What do you need to know before you can make a decision, or that will help you make the right one?

3: Analyzing the situation

What alternative courses of action may be available to you? What different interpretations of the data may be possible? Our Problem Solving Activity uses a set of structured questions to encourage both broad and deep analysis of your situation or problem.

4: Developing options

Generate several possible options. Be creative and positive. Read The Power of Positive Thinking for our five questions that create possibilities.

5: Evaluating alternatives

What criteria should you use to evaluate? Evaluate for feasibility, acceptability and desirability. Which alternative will best achieve your objectives?

6: Selecting a preferred alternative

Explore the provisional preferred alternative for future possible adverse consequences. What problems might it create? What are the risks of making this decision?

7: Acting on the decision

Put a plan in place to implement the decision. Have you allocated resources to implement? Is the decision accepted and supported by colleagues? Are they committed to making the decision work?
Competence & Mental Status


UNC School of Government (28 Pages)

https://www.sog.unc.edu/sites/default/files/course_materials/HillCompetenceMentalStatus.pdf

Competency is a legal concept; it refers to having the. 'mental capacity to decide in accordance with one's goals, concerns and values'.


What are the elements of competence?

What are the 5 components of competency?

AI Overview

The five core elements of individual competency in professional and management frameworks are knowledge, skills, attitude (or behavior), personal characteristics, and experience.


The 5 Core Components

Knowledge:

The facts, theories, and ideas you understand about your job or industry.

Skills:

The practical abilities and technical tools you use to perform tasks.

Attitude / Behavior:

Your mindset, work ethic, and how you approach challenges and interact with others.

Personal Characteristics:

Your natural traits, emotional intelligence, and personal qualities that shape how you react.

Experience:

The practical background and past time spent applying your abilities in real situations.


(Note: In education and training design, the "5 components of competency-based education" instead refer to outcome frameworks, developmental progression, tailored learning, competency-focused coaching, and programmatic assessment.)


Competency - There are 4 ‘accepted’ standard elements:


  • Communication of choice
  • Understanding of information
  • Appreciation of one’s situation & risks/benefits of choices made
  • Rational decision-making


Courts prefer the first two, psychiatry the latter


Self-scored by Keith “Buster” Torkelson
MAiD Competence 17 Items
HSF = High Scores are Favorable


Side - Oswaldo Escalante
https://www.linkedin.com/in/oswaldo-escalante-024a6018
LinkedIn · Oswaldo Escalante
90+ followers
Downey, California, United States
Student Services Specialist · Lynwood Unified School District
Brand New Day - Nov 2011 - Aug 2014 2 years 10 months
Recovery Counselor - Behavioral Health Services, Inc. Jan 2009


Compare

Oswaldo Escalante

Mr. Oswaldo O. Escalante is recognized for his expertise as a student services specialist and counselor for the Student Services Department for the Lynwood Unified School District. Compton/Lynwood, CA, February 15, 2023 - Oswaldo O. Escalante has been included in Marquis Who's Who. As in all Marquis Who's Who biographical volumes, individuals profiled are selected on the basis of current reference value. Factors such as position, noteworthy accomplishments, visibility, and prominence in a field are all taken into account during the selection process.

FYI

https://www.24-7pressrelease.com/press-release/498441/oswaldo-o-escalante-has-been-inducted-into-the-prestigious-marquis-whos-who-biographical-registry


Jeff Gibbs

Jeff Gibbs is a Mental Health Rehab Specialist (MHRS) and Social Service professional who worked at Brand New Day for over 11 years (June 2011 – Dec 2022). He specializes in social services and, according to LinkedIn, is based in the Los Angeles area, often involved in supporting mental health and community wellbeing.


Digital Presence (Case workers – Care coordinators)
Escalante > Reynolds > Gibbs
Jessica Reynolds Brand New Day on Facebook


The Clinic – Central City Community Health Center – Garden Grove


Mentalation Solutions Group – Keith Torkelson MS
 
Global Link (To Current)
https://housingadvisoryboard.blogspot.com
 
Aside – Work Done
20191023-W: Housing Advisory – by Keith Torkelson
https://housingadvisoryboard.blogspot.com/2019/10/20191023-w-housing-advisory-by-keith.html
Oct 23, 2019
We are Mentalation Solutions Group (MSG). Dozens of Images


Effort

We are Mentalation Solutions Group (MSG) and we engage in Advocacy and External Quality Review efforts about Health & Human Services. Our specialty is Thanatology.


Central City Community Health Center's Online Review Report

ScoreDoc
https://www.scoredoc.com/ca/garden-grove/central-city-community-health-center/review-report-card/1580219/2641843
20260424-F: Average Star Rating = 1.7 | Total Reviews = 22
20260917-TH- Average Star Rating = 1.7 | Total Reviews = 22


Sample Review (EQR)

We are Mentalation Solutions Group (MSG) and we engage in Advocacy, and External Quality Review, efforts about Health & Human Services. Keith was first served by Martha G Gil a Central City RN during the summer of 2012.  She was primarily Keith’s phlebotomist.  We gave her a stellar review for her service for year 2018.  Currently, 2026, we give Central City a Quick Stars Score of 4.5 of 5.0 Stars with 5.0 being Excellent.


Autobiographical – Was I and am I Competent?
Super Bios (Medium)
https://ktork46.blogspot.com/2016/12/keith-edward-torkelson-ms-super-bios.html
 
Curriculum Vitae (Long)
https://ktork46.blogspot.com/2013/01/keith-torkelson-curriculum-vitae.html
 
2018 Bios (Short)
https://the-torkel-saga-2059.blogspot.com/2018/04/keith-edward-torkelson-ms-2018-bios.html
 
Scored by and for Keith “Buster” Torkelson on 20160615-W
Progressive Competency Evaluation 16 Items
(MSG-Derived)


Comrade: Would I work with this helper? 
ND = Not Demonstrated (Scores as a FAIL)
 
Scored by and for Keith “Buster” Torkelson, MS on 20160615-W
Progressive Competency Scale 15 Items
(MSG-Derived)


Scored by and for Keith “Buster” Torkelson on 20160615-W
Progressive Competency Performance 18 Items
(MSG-Derived)


Scored by and for Keith “Buster” Torkelson on 20160615-W
Progressive Stages 6 Items
(MSG-Derived)


How is it good help is hard to get and keep for non-profits?

Non-profits struggle to get and keep help due to chronic funding restrictions, low salaries, and high burnout, often creating a "survival mentality". High staff turnover—especially in fundraising—averages just 16 months, breaking critical donor relationships. This scarcity makes it hard to afford talent or build long-term capacity.


How is it inferior case workers?

"Inferior" caseworkers, or more accurately, ineffective or "bad" caseworkers, are often created by systemic pressures, lack of training, and high burnout rather than just individual malice. According to user experiences and professional analyses, they are characterized by behaviors that fail to protect or support families. The term inferior case workers does not refer to a standard professional classification, but rather describes cases where a case worker's performance, resources, or systemic support fall below acceptable standards. In social work, healthcare, and legal systems, case workers are considered ineffective or "inferior" when specific systemic or individual failures compromise client care.

Scored by and for Keith “Buster” Torkelson on 20160708-F
(MSG-Derived)
Professional Competencies Gaps 27 Items
IP = In Progress


Does the quality and competence of your care coordinator matter?

Yes, the quality and competence of a care coordinator are critical because they directly impact patient health outcomes, continuity of care, and safety. A competent coordinator reduces fragmented care, manages complex needs, and improves patient satisfaction, while skilled coordination can improve outcomes for individuals with multiple chronic conditions.


In House > Metadata >
Outcomes for RDA-Modified Partnership Assessment
MSG-RDA-PV (16 Items)
Assess_Partnership_RDA_16070202_Gibbs V2026 (Has Assessment & Results)
 
Table - Resource Development Associates (RDA) - Modified
Date Finalized: 20160821-SU
Calculations – Yields Partnership RDA Value
Scored by Keith “Buster” Torkelson, MS
HSF = High Scores are Favorable | Kline = Lanaii Kline (Oldest sister)


FYI – Aside - Mental Health Assessment (2012 - 208 Pages)

https://www.drugsandalcohol.ie/17625/1/MentalHealthAssessmentTools.pdf

Includes 30 Assessment Tools

*redacted due to copyright


Section 1: Mental Health Screening Tools (Page Number)

  • Mini-Mental State Examination (MMSE) 11
  • KGV (Modified) Symptom Scale 17
  • Risk Assessment Summary Department of Psychiatry, Portlaoise 65
  • Risk Assessment Tool Longford/Westmeath MHS 66
  • Depression/Anxiety/Stress Scale (DASS) 67
  • PSYRATS – Hallucinations Subscale 75
  • PSYRATS – Delusions Subscale 81
  • Geriatric Depression Scale (GDS) 87
  • Beck’s Depression Inventory (BDI) (*redacted) 91
  • Beck’s Suicidal Intent Scale (BSIS) (*redacted) 95
  • Beck’s Hopelessness Scale (BHS) (*redacted) 101
  • Beck’s Anxiety Inventory (BAI) (*redacted) 104
  • Anxiety Rating Scale (Zung) 107
  • Rosenberg Self Esteem Scale 109
  • Evaluative Belief Scale 112
  • Sleep Scale 114


Section 2: Medication Related Screening Tools

  • LUNSERS – Side-effect rating scale 119
  • DAI - Drug Attitude Inventory (DAI 30) 127


Section 3: Addiction Screening Tools

  • MAST - Michigan Alcohol Screening Tool (MAST 25) 131
  • DAST - Drug Abuse Screening Tool (DAST 20) 135
  • AUDIT – The Alcohol Use Disorders Identification Test 137
  • CAGE - Alcohol Misuse Screening Tool 141


Section 4: Living Skills Screening Tools

  • Life Skills Profile (LSP 20) 145
  • Social Functioning Scale (SFS) 157
  • BARTHEL Index of Daily Living 175
  • Social Network Map (SNM) 177
  • Camberwell Assessment of Need (CAN) 180
  • Relative Assessment Interview (RAI) 190


The Meaning of Redacted

Redacted means that specific words, numbers, or sections have been deliberately removed, blocked out, or hidden from a document before it is shared with the public.

Why Documents Are Redacted

Privacy protection:

Hiding personal details like social security numbers, birth dates, or addresses.

Legal compliance:

Removing names of minors, trade secrets, or protected health data.

National security:

Concealing classified government or military secrets.

Ongoing investigations:

Blocking details that might interfere with an active police case.

Common Methods

Blacking out:

Covering text with solid black bars.

Labeling:

Replacing text with brackets like [REDACTED].

Digital scrubbing:

Permanently stripping hidden metadata and underlying text layers so the data cannot be recovered.


FYI – AI - You can test or apply these censoring effects yourself using free online tools like Redacted.

Would you like to know how to properly redact a PDF or digital document, or are you looking for information on a specific redacted government record or case?

 
Informed Consent – Competence


The Hopkins Competency Assessment Test: A Brief Method for Evaluating Patients’ Capacity to Give Informed Consent


FYI - The Hopkins Competency Test - Jeffrey S. Janofsky, M.D.

http://www.jeffreyjanofsky.com/media/pdf/The-Hopkins-Competency-Assessment-Test.pdf

by JS Janofsky · 1992 · Cited by 349

The Hopkins Competency Assessment Test (HCAT), a brief instrument for evaluating the competence of patients to give informed consent or write advance directives, consists of a short essay and a questionnaire for determining patients’ understanding of the essay. In a study to validate the instrument, 41 medical and psychiatric inpatients answered the questionnaire after reading the essay while hearing it read aloud. A forensic psychiatrist who was blind to the HCAT scores later examined the patients for competency. A subject’s number of correct answers to the HCAT questionnaire was an accurate indicator of clinical competency as assessed by the psychiatrist. The results suggest that the HCAT is a useful too/for rapidly screening patients for competency to make treatment decisions.


Grounds for LSP Conservatorship

An LPS (Lanterman-Petris-Short) conservatorship in California is established for adults with severe mental illnesses (listed in the DSM) who are deemed "gravely disabled"—meaning they are unable to provide for their own basic needs for food, clothing, or shelter due to that illness. It requires proof of a current, treatable mental disorder and is designed to provide involuntary treatment or secure placement, usually lasting one year, often for those non-compliant with treatment.


Key Grounds for LPS Conservatorship

Grave Disability

The primary requirement is that the person is, as a result of a mental disorder, unable to provide for their own basic personal needs (food, clothing, or shelter).

Specific Mental Disorder

The disability must stem from a mental illness defined by the Diagnostic and Statistical Manual of Mental Disorders (DSM), such as schizophrenia, bipolar disorder, or schizo-affective disorder.

Inability to Accept Treatment

The person is unwilling or incapable of accepting voluntary treatment.

Chronic Alcoholism

In some cases, severe, disabling chronic alcoholism may be grounds.

What "Gravely Disabled" Means

Safety Risk

The individual cannot live safely on their own, often due to an inability to manage nourishment or hygiene.

Not Just Homelessness

Being homeless alone does not meet the criteria; it must be a direct result of mental illness rendering them unable to seek food or shelter.

Current Danger

The person must be a present danger to themselves, not just a future risk.


Key Considerations
LPS - Duration
Lasts one year, renewable annually.


Process

Requires a court hearing, which may involve a jury trial if requested, where the, burden of proof is beyond a reasonable doubt.

Rights

The conservator may have the power to place the individual in a locked facility and make mental health treatment decisions, including medication.


Why are skilled nursing facilities locked facilities?

Skilled nursing facilities use locked doors primarily to protect residents who are at risk of wandering or leaving unsafely due to cognitive decline or memory loss.

Reasons for Locking Doors

Preventing Elopement:

Residents with dementia or Alzheimer's disease may wander off, get lost, or put themselves in severe physical danger from traffic, weather, or falls.

Clinical and Safety Needs:

Regulations like the Life Safety Code permit facilities to lock specific doors when it addresses the direct clinical or safety needs of the residents.

Managing Distressed Behavior:

Securing units helps protect individuals who experience severe disorientation, delusions, or agitation that impairs their judgment.

Legal and Ethical Boundaries

Not Entirely Locked:

Whole buildings are rarely locked down entirely; restrictions are usually confined to specialized memory care units or specific exit points.

Resident Rights:

Residents who are legally and mentally competent retain the right to come and go, and facilities cannot involuntarily hold them without proper legal or medical authorization.


FYI – AI - If you'd like, I can provide more information on: The difference between skilled nursing and memory care access rules. How facilities balance resident autonomy with safety


Mental Health Competency

Mental health competency refers to an individual's capacity for rational decision-making regarding their care, involving understanding, appreciating, reasoning, and expressing choices, while for professionals, it means skills in communication, crisis intervention, person-centered care, ethics, and cultural responsiveness to support others. It's a fluid concept, assessed in specific contexts (like legal or medical), and involves foundational elements for general well-being and thriving despite challenges.

For Individuals (Decision-Making Capacity)

  • Understanding
  • Grasping the situation, information, risks, and benefits.
  • Appreciation
  • Recognizing the personal significance of the information.
  • Reasoning
  • Applying information logically to their situation.
  • Expressing a Choice
  • Clearly communicating a preference or decision.


For Mental Health Professionals (Core Competencies)


Communication & Person-Centered Care
Using effective skills and a tailored approach.
 
Crisis Management
Preventing and intervening in crises.
 
Ethics & Professionalism
Upholding standards, promoting advocacy, and ensuring safety.
 
Cultural & Diversity
Applying multicultural competencies.
 
Health & Wellness
Integrating mental health into overall care.
 
Self-Development
Continuous learning and training.


Key Aspects 

Context-Specific

Context-specific competency, particularly regarding decision-making capacity, is generally understood to be task-specific, fluid, and situational rather than a global, all-or-nothing trait. A person may be considered competent to make one type of decision (e.g., daily activities) while lacking the capacity for more complex decisions (e.g., financial management or major medical treatment) at the same time.

Fluid

It can change over time due to illness, treatment, or life events.

Foundation for Well-being

Beyond disorders, it involves resilience, coping, and functioning well.


Standardized Instruments

Mental competency assessment tools are specialized, standardized instruments—such as the MacArthur Competence Assessment Tool (MacCAT-CA) for legal contexts or the Mini-Mental State Examination (MMSE) for cognitive screening—designed to evaluate a person's ability to understand information, make decisions, and communicate choices. These tools are used in forensic, clinical, and social care settings to measure cognitive function, legal capacity, or capacity to make decisions regarding care.


FYI - The Mini Mental State Examination (MMSE) – 2 Pages

https://cgatoolkit.ca/Uploads/ContentDocuments/MMSE.pdf

By L Kurlowicz · Cited by 445 — It is an 11-question measure that tests five areas of cognitive function: orientation, registration, attention and calculation, recall, and language.


Appendix – BHSA Values Mission Vision

The California Behavioral Health Services Act (BHSA) (formerly the Mental Health Services Act) has a core mission, vision, and set of values aimed at transforming state behavioral health care.

Vision

To build an equitable, integrated, and responsive behavioral health system where all Californians—especially those with the most serious mental health and substance use disorder (SUD) needs—have access to coordinated care, housing, and support to promote recovery, stability, and overall well-being.

Mission

To modernize and reform California's behavioral health system by prioritizing early intervention, community-based services, treatment for mental health and substance use disorders, housing solutions, and workforce expansion while maximizing transparency, equity, and accountability at both state and local levels.

Core Values

Equity & Inclusion:

Eliminating disparities in care and ensuring culturally competent services reach historically underserved and vulnerable populations.

Accountability & Transparency:

Tracking outcomes, ensuring responsible stewardship of public funds, and maintaining clear oversight at state and local levels.

Compassion & Person-Centered Care:

Focusing on whole-person wellness, early intervention, and actively supporting individuals and their families along the path to recovery.

Collaboration:

Partnering across communities, schools, state departments, and local agencies to connect services seamlessly.

Innovation:

Expanding workforce capacity and adopting modern, evidence-based approaches (such as school-linked mental health and integrated substance use supports).

FYI – AI - If you are looking for information specific to a particular county's implementation or need details on the Three-Year Integrated Plan for BHSA in your area, let me know!